yearadmit
admit 时间:2021-01-25 阅读:()
GeertMeyfroidtPierre-EdouardBollaertPaulE.
MarikAcuteischemicstrokeintheICU:toadmitornottoadmitReceived:1April2014Accepted:1April2014Publishedonline:8April2014Springer-VerlagBerlinHeidelbergandESICM2014G.
Meyfroidt())IntensiveCareMedicine,KULeuven,Line1:UZLeuven,3000Louvain,Belgiume-mail:geert.
meyfroidt@uzleuven.
beP.
-E.
BollaertServicedeReanimationMedicale,CHUdeNancy,Nancy,FranceP.
E.
MarikEasternVirginiaMedicalSchool,Norfolk,VA,USAAcuteischemicstroke(AIS)isanimportanthealth-careproblemworldwide,andasignicantcauseofdisabilityaswellasmortality.
TheincidenceofAISisexpectedtoincreaseinthefuture,becausethemajorityofAISarecausedbycardio-embolicdisordersandatherosclerosis,typicalfortheageingpopulation.
OnlytwointerventionsinsmallsubsetsofpatientshavebeendemonstratedtoimprovetheoutcomeofAISpatients.
ThesinglemostimportantinterventiontoalterthenaturalhistoryofAISandimprovethepatients'functionaloutcomeisthetimelyadministrationofathrombolyticagent(intra-venousrt-PA)intheappropriatepatientwithinthenarrow4.
5-hwindow[1].
Endovasculartherapyrepresentsanalternativetherapytointravenousrt-PAinthosewhoarenotcandidatesforintravenousrt-PA,buthasnoadvantageoverintravenousrt-PA[2].
Hemisphericdecompressioninpatientslessthan60yearsofagewithmalignantmiddlecerebralarteryterritory(MCA)infarctionandspace-occu-pyingbrainoedemahasbeendemonstratedtoimproveoutcome.
Thisresultwasconrmedinanindividualpatientmeta-analysis,demonstratingamarkedimprovementinneurologicalrecoveryandsurvival[3].
Fortheagegroupolderthan60yearsofagewithmalignantMCAinfarction,whoareover-representedintheAISpatientgroup,therecentlypublishedDESTINYIItrialwasabletodemon-stratethatdecompressionwasalsoabletoreducemortality,butnotinuencetheproportionofpatientswithseveredisability[4].
Despiteinitialpromise,neuroprotectiveagentshavefailedtoshowabenetinthemanagementofAIS[5],ashavetightglycaemiccontrol[6],highdosealbumin[7]andtheuseofanti-hypertensiveagents[8,9].
Today,increasingnumbersofpatientswithAISareadmittedtoanintensivecareunit(ICU)forvariousindi-cations.
InthisissueofIntensiveCareMedicine,Kirkmanetal.
presentastateoftheartreviewoftheICUmanage-mentofpatientswithAIS[10].
Theirreviewisverythoroughandprovideskeyrecommendationsontheaforementionedinterventions.
Unfortunately,theywerenotabletoprovidemuchevidence-basedguidanceastowhichpatientsshouldbeadmittedtotheICU,andwhichsubgroupsofAISpatientscouldactuallybenetfromICUmanagement.
TheguidelinesoftheSocietyofCriticalCareMedicinestatethat''ingeneralICUsshouldbereservedforthosepatentswithreversiblemedicalconditionswhohaveareasonableprospectofsubstantialrecovery''[11].
InherentinthisguidelineasitappliestotheAISpatient,istheassumptionthattheintensivisthasanarsenaloftherapeuticinterventionswhichwillalterthecourseofthepatient'sstrokeandthattheseinterventionswillimprovethepatient'soutcome.
IfwetakealookatthedataonmechanicalventilationinAISpatients,probablyoneofthemainindicationsforreferraltoanICU,notsurprisingly,therequirementformechanicalventilationinitselfappearstobeassociatedwithbothahighershort-andlong-termmortality.
Usingalargeadministrativedatabasecovering93countiesintheeasternhalfoftheUSA,Golestanianetal.
[12]evaluatedtheoutcomesof31,301AISpatients.
The30-dayand1-yearmortalitywas64%and81%respec-tivelyinthosepatientswhorequiredmechanicalventilationcomparedto16%and35%inthosepatientswhodidnotrequiremechanicalventilation.
Anumberofsmallerstud-ies(lessthan100patientseach)haveaddressedthisquestionaswell.
ThesestudiesconrmedtheobservedhighIntensiveCareMed(2014)40:749–751DOI10.
1007/s00134-014-3289-5EDITORIAL1-yearmortalityforpatientsrequiringmechanicalventi-lation,37–87%,withnoclearevidenceofimprovementovertime[13–18].
Furthermore,severedisabilitywasobservedin20–45%ofsurvivors.
InthisdiscussiononthebenetofmechanicalventilationfortheoutcomeofAIS,thereasonwhymechanicalventilationwasinitiatedmightbeimportant.
Unfortunately,thiswasonlyassessedinfourofthesestudies(Fig.
1)[13–16].
Althoughthepopulationsamplesincludedinthelatterstudiesweresmall,thesedatasuggestthatthosepatientsintubatedandventilatedforcomaorneurologicdeteriorationmaynotbenetfrommechanicalventilation.
Thelackofdataontheoutcomebenetofspecicther-apeuticinterventionstoimprovetheoutcomeofthemajorityofpatientssufferingfromAIScertainlydoesnotimplythatphysiciansshouldadoptafatalisticapproachwhenmanag-ingthesepatients.
Anumberofwell-conductedclinicaltrialshavedemonstratedthatthemortalityandfunctionalrecoveryofpatientsfollowingastrokearesignicantlyimprovedwhenthesepatientsarecaredforinaspecializedstrokeunitascomparedtoageneralmedicalward[19,20].
Theseunitsprovidespecializednursingcareandawell-organizedmul-tidisciplinaryrehabilitationprogram.
Strokeunitcarereducesthemedicalcomplicationsinthesepatientsandallowsforearlierandmoreintenserehabilitation.
Incontrasttothis,specicstrokeICUswereaban-donedinthe1970safteritwasdemonstratedthatsuchunitshadverylittleimpactontheoutcomeofpatientsfollowingastroke.
Nevertheless,aproportionofpatientswhosufferfromstrokemaybenetfromadmissiontotheICU.
Endotrachealintubationandmechanicalventilationshouldbereservedforpatientswithreversiblerespiratoryfailurewhoarelikelytohaveagoodprognosisforafunctionalrecovery,e.
g.
inthetreatmentandpreventionofaspirationpneumoniaduetotemporallossofbulbarfunction,occurringin37–78%ofstrokepatients[21].
LargeMCAstrokeswhomayrequiredecompressivecraniectomy,regardlessoftheirage[3,4],andspace-occupyingcerebellarinfarctionsaccessibletoapromptsurgicaldecompression[22]areaclearindicationforICUadmission.
Insomecases,themanagementofbloodpressure,orseizures,mightnecessitateanICUadmission.
FurtherresearchshouldfocusontheuseofvalidatedstrokeseverityscoringsystemssuchastheNIHStrokeScale(NIHSS)ortheTriageStrokePanel(MMX),takingintoaccounttheinitialclinicalevolutionofthesepatients[23],toidentifythosepatientswhowillbenetfromICUreferral.
Itisclearthataggressivemedicalmeasuresindeeplycomatosepatients,withalowprobabilityofafavourableoutcomeareaformofnon-benecialcare,whichwillonlyincreasetheburdenonpatients,familiesandthehealth-caresystem.
Theparadigmof''lessmaybemore''wouldappeartobeappropriateforthesepatients[24].
References1.
LeesKR,BluhmkiE,vonKR,BrottTG,ToniD,GrottaJC,AlbersGW,KasteM,MarlerJR,HamiltonSA,TilleyBC,DavisSM,DonnanGA,HackeW(2010)Timetotreatmentwithintravenousalteplaseandoutcomeinstroke:anupdatedpooledanalysisofECASS,ATLANTIS,NINDS,andEPITHETtrials.
Lancet375:1695–17032.
CicconeA,ValvassoriL,NichelattiM,SgoifoA,PonzioM,SterziR,BoccardiE(2013)Endovasculartreatmentforacuteischemicstroke.
NEnglJMed368:904–9133.
VahediK,HofmeijerJ,JuettlerE,VicautE,GeorgeB,AlgraA,AmelinkGJ,SchmiedeckP,SchwabS,RothwellPM,BousserMG,vanderWorpHB,HackeW(2007)Earlydecompressivesurgeryinmalignantinfarctionofthemiddlecerebralartery:apooledanalysisofthreerandomisedcontrolledtrials.
LancetNeurol6:215–2220102030405060708090100Burtinetal.
Wijdicksetal.
Steineretal.
Lekeretal.
ComaConvulsionsElectiveResp.
failure%1-yearmortalityFig.
1One-yearmortalityinstrokepatientsaccordingtothecauseofmechanicalventilation7504.
Ju¨ttlerE,UnterbergA,WoitzikJ,Bo¨selJ,AmiriH,SakowitzOW,GondanM,SchillerP,LimprechtR,LuntzS,SchneiderH,PinzerT,HobohmC,MeixensbergerJ(2014)HackeWfortheDESTINYIIInvestigators.
Hemicraniectomyinolderpatientswithextensivemiddlecerebralarterystroke.
NEngJMed370:1091–11005.
GinsbergMD(2008)Neuroprotectionforischemicstroke:past,presentandfuture.
Neuropharmacology55:363–3896.
RossoC,CorvolJC,PiresC,CrozierS,AttalY,JacqueminetS,DeltourS,MultluG,LegerA,MeresseI,PayanC,DormontD,SamsonY(2012)Intensiveversussubcutaneousinsulininpatientswithhyperacutestroke:resultsfromtherandomizedINSULINFARCTtrial.
Stroke43:2343–23497.
GinsbergMD,PaleschYY,HillMD,MartinRH,MoyCS,BarsanWG,WaldmanBD,TamarizD,RyckborstKJ(2013)High-dosealbumintreatmentforacuteischaemicstroke(ALIAS)part2:arandomised,double-blind,phase3,placebo-controlledtrial.
LancetNeurol12:1049–10588.
HeJ,ZhangY,XuT,ZhaoQ,WangD,ChenCS,TongW,LiuC,XuT,JuZ(2014)Effectofimmediatebloodpressurereductionondeathandmajordisabilityinpatientswithacuteischemicstroke:theCATISrandomizedclinicaltrial.
JAMA311:479–4899.
HankeyGJ(2011)Loweringbloodpressureinacutestroke:theSCASTtrial.
Lancet377:696–69810.
KirkmanMA,CiterioG,SmithM(2014).
Theintensivecaremanagementofacuteischemicstroke:anoverview.
IntensiveCareMed.
doi:10.
1007/s00134-014-3266-z11.
TaskForceoftheAmericanCollegeofCriticalCareMedicine,SocietyofCriticalCareMedicine(1999)Guidelinesforintensivecareunitadmission,discharge,andtriage.
CritCareMed27:633–63812.
GolestanianE,LiouJI,SmithMA(2009)Long-termsurvivalinoldercriticallyillpatientswithacuteischemicstroke.
CritCareMed37:3107–311313.
BurtinP,BollaertPE,FeldmannL,NaceL,LelargeP,BauerP,LarcanA(1994)Prognosisofstrokepatientsundergoingmechanicalventilation.
IntensiveCareMed20:32–3614.
SteinerT,MendozaG,DeGeorgiaM,SchellingerP,HolleR,HackeW(1997)Prognosisofstrokepatientsrequiringmechanicalventilationinaneurologicalcriticalcareunit.
Stroke28:711–71515.
WijdicksEF,ScottJP(1997)Causesandoutcomeofmechanicalventilationinpatientswithhemisphericischemicstroke.
MayoClinProc72:210–21316.
LekerRR,Ben-HurT(2000)Prognosticfactorsinarticiallyventilatedstrokepatients.
JNeurolSci176:83–8717.
SantoliF,DeJB,HayonJ,TranB,PiperaudM,MerrerJ,OutinH(2001)Mechanicalventilationinpatientswithacuteischemicstroke:survivalandoutcomeatoneyear.
IntensiveCareMed27:1141–114618.
Navarrete-NavarroP,Rivera-FernandezR,Lopez-MutuberriaMT,GalindoI,MurilloF,DominguezJM,MunozA,Jimenez-MoragasJM,NacleB,Vazquez-MataG(2003)Outcomepredictionintermsoffunctionaldisabilityandmortalityat1yearamongICU-admittedseverestrokepatients:aprospectiveepidemiologicalstudyinthesouthoftheEuropeanUnion(EvascanProject,Andalusia,Spain).
IntensiveCareMed29:1237–124419.
StrokeUnitTrialists'Collaboration(2013)Organisedinpatient(strokeunit)careforstroke.
CochraneDatabaseSystRev9:CD00019720.
LanghorneP,deVilliersL,PandianJD(2012)Applicabilityofstroke-unitcaretolow-incomeandmiddle-incomecountries.
LancetNeurol11:341–34821.
MartinoR,FoleyN,BhogalS,DiamantN,SpeechleyM,TeasellR(2005)Dysphagiaafterstroke:incidence,diagnosisandpulmonarycomplications.
Stroke36:2756–276322.
JuttlerE,SchweickertS,RinglebPA,HuttnerHB,KohrmannM,AschoffA(2009)Long-termoutcomeaftersurgicaltreatmentforspace-occupyingcerebellarinfarction:experiencein56patients.
Stroke40:3060–306623.
BrounsR,SheorajpandayR,KunnenJ,DeSurgelooseD,DeDeynPP(2009)Clinical,biochemicalandneuroimagingparametersafterthrombolytictherapypredictlong-termstrokeoutcome.
EurNeurol62(1):9–1524.
KnoxM,PickkersP(2013)''Lessismore''incriticallyillpatients:nottoointensive.
JAMAInternMed173:1369–1372751
- yearadmit相关文档
- 13.8admit
- 二零一八聖誕及新年燈飾佈置工程(第二期)
- Questionadmit
- Engineeringadmit
- boundadmit
- 94.9626752865208admit
云如故枣庄高防(49元)大内存2H2G49元8H8G109元
云如故是一家成立于2018年的国内企业IDC服务商,由山东云如故网络科技有限公司运营,IDC ICP ISP CDN VPN IRCS等证件齐全!合法运营销售,主要从事自营高防独立服务器、物理机、VPS、云服务器,虚拟主机等产品销售,适合高防稳定等需求的用户,可用于建站、游戏、商城、steam、APP、小程序、软件、资料存储等等各种个人及企业级用途。机房可封UDP 海外 支持策略定制 双层硬件(傲...

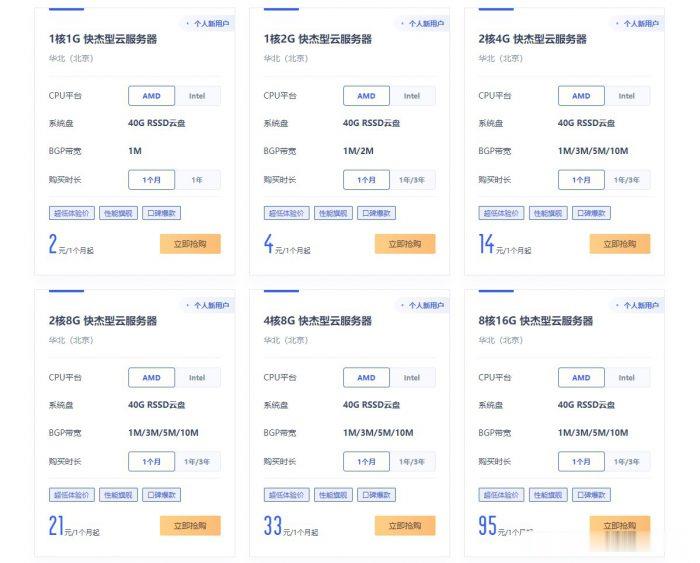
ucloud国内云服务器2元/月起;香港云服务器4元/首月;台湾云服务器3元/首月
ucloud云服务器怎么样?ucloud为了扩大云服务器市场份额,给出了超低价云服务器的促销活动,活动仍然是此前的Ucloud全球大促活动页面。目前,ucloud国内云服务器2元/月起;香港云服务器4元/首月;台湾云服务器3元/首月。相当于2-4元就可以试用国内、中国香港、中国台湾这三个地域的云服务器1个月了。ucloud全球大促仅限新用户,国内云服务器个人用户低至56元/年起,香港云服务器也仅8...
ZJI(月付480元),香港阿里云专线服务器
ZJI是成立于2011年原Wordpress圈知名主机商—维翔主机,2018年9月更名为ZJI,主要提供香港、日本、美国独立服务器(自营/数据中心直营)租用及VDS、虚拟主机空间、域名注册业务。本月商家针对香港阿里云线路独立服务器提供月付立减270-400元优惠码,优惠后香港独立服务器(阿里云专线)E3或者E5 CPU,SSD硬盘,最低每月仅480元起。阿里一型CPU:Intel E5-2630L...
admit为你推荐
-
桌面背景图片淡雅为什么好看的图片用来做桌面背景图就会很模糊?苹果x和xr哪个好苹果xr好还是苹果x好录屏软件哪个好什么录屏软件好用莫代尔和纯棉哪个好请问莫代尔棉和纯莫代尔哪个更好?手动挡和自动挡哪个好手动档与自动档哪个好?无纺布和熔喷布口罩哪个好医用 口罩里面是无纺布好还是过滤纸好红茶和绿茶哪个好红茶和绿茶哪个比较好?qq网盘在哪里QQ网盘在哪里dns服务器未响应dns 服务器未响应 怎么解决上海dns服务器地址上海市青浦区的电信DNS地址是多少