nauseawww.aise.com
www.aise.com 时间:2021-03-20 阅读:()
CASEREPORTOpenAccessDrugreactionwitheosinophiliaandsystemicsymptomssyndromeinapatienttakingphenytoinandlevetiracetam:acasereportDavidJeffreyHall1andJasonStevenFromm2*AbstractIntroduction:Drugreactionwitheosinophiliaandsystemicsymptomssyndromeisapotentiallylife-threateninghypersensitivityreactionwithrash,fever,andinternalorganinvolvement,oftenhepatitis,occurringmostcommonlytwotoeightweeksafterinitiationofamedication.
Thepresentcaseisanexampleofsevereandpotentiallylife-threateninghepatitisasamanifestationofdrugreactionwitheosinophiliaandsystemicsymptomssyndrome.
Casepresentation:Wereportacaseofanti-epileptic-induceddrugreactionwitheosinophiliaandsystemicsymptomssyndromeinan18-year-oldAfrican-Americanmanwhopresentedwithafive-dayhistoryofrash,periorbitalandupperextremityedema,hepatitisandfever.
Laboratoryfindingsrevealedanatypicallymphocytosis,eosinophilia,andelevatedserumtransaminases.
Nodrugallergieswerereportedatthetimeofpresentation,butphenytoinandlevetiracetamtherapyhadbeeninitiatedfiveweekspriortohospitaladmissionfornew-onsetseizures.
Bothmedicationswerediscontinuedonhospitaladmission,andafterthreedaysofhigh-dosecorticosteroidtherapythepatientexperiencedresolutionofbothhissymptomsandlaboratorymarkersofinflammation.
Conclusion:Giventhesignificantmortalityattributedtodrugreactionwitheosinophiliaandsystemicsymptomssyndrome,medicalpersonnelshouldbeawareofthepotentialforthisseverehypersensitivityreactionandshouldensureclosefollow-upandofferanticipatoryguidancewhenbeginninganynewmedication,particularlyanti-epileptictherapy.
Earlyrecognitionofdrugreactionwitheosinophiliaandsystemicsymptomssyndromeandinitiationofappropriatetherapyareimperativeinlimitingmorbidity.
Keywords:Allergy,Anti-epileptic,DRESSsyndrome,Hepatitis,Hypersensitivityreaction,LevetiracetamPhenytoin,RashIntroductionDrugreactionwitheosinophiliaandsystemicsymptoms(DRESS)syndrome,alsoknownasdrug-inducedhy-persensitivitysyndrome(DIHS),isanunder-recognizedandpotentiallylife-threateninghypersensitivityreactionassociatedwithavarietyofmedications,manybeinganti-epileptics.
PatientswithDRESSsyndrometypicallypresentwithrash,swelling,fever,andsystemicmanifes-tationssuchasaseveretransaminitis[1].
Inmostcases,apatient'sface,trunk,andupperextremitiesareaffectedbyarashwhichisatfirstmorbilliformthengraduallytransitionstomaculopapular,andfinallycanprogresstoedemaoftheface,particularlyintheperiorbitalregion.
Althoughrashandeosinophiliaarecommonlyseeninhypersensitivityreactions,thedefiningcharacteristicofDRESSsyndromeisorgandysfunction,mostcommonlyoftheliver,kidneys,heart,orlungs.
Thesepatientsaretypicallyfoundtohavestartedoneofafewselectmedi-cationsinthepasttwotoeightweeks(Table1)witharo-maticanti-epilepticsbeingthemostcommonlyimplicated[2-6].
Non-aromaticanti-epilepticmedica-tionssuchasatopiramate,ethosuximide,andlevetirace-tamweretraditionallythoughttobesafer;however,arecentcasereportdescribedDRESSsyndromeinapa-tienttakingonlylevetiracetam[7].
Althoughthetruein-cidenceisunknown,DRESSsyndromehasbeen*Correspondence:jason.
fromm@medicine.
ufl.
edu2DepartmentofMedicine,UniversityofFloridaCollegeofMedicine,1600SWArcherRoad,POBox100277,Gainesville,FL32610-0277,USAFulllistofauthorinformationisavailableattheendofthearticleJOURNALOFMEDICALCASEREPORTS2013HallandFromm;licenseeBioMedCentralLtd.
ThisisanOpenAccessarticledistributedunderthetermsoftheCreativeCommonsAttributionLicense(http://creativecommons.
org/licenses/by/2.
0),whichpermitsunrestricteduse,distribution,andreproductioninanymedium,providedtheoriginalworkisproperlycited.
HallandFrommJournalofMedicalCaseReports2013,7:2http://www.
jmedicalcasereports.
com/content/7/1/2estimatedtooccurinapproximatelyoneoutof1000to10,000newusersofanti-epilepticmedicationsandismorecommonlyreportedinAfrican-Americanmen[1,8,9].
VitaminDdeficiencyhasbeenimplicatedasapossiblecontributortothepathogenesisofDRESSduetoitsprotectiveeffectsagainstinflammatoryandauto-immuneconditions,andbecausevitaminDdeficiencyoccursmorefrequentlyinpeoplewithdarkerskinphenotypes[10].
DIHSwasoriginallydescribedin1950byChaikenetal.
asatriadoffever,rash,andmulti-organfailure[11].
TheacronymDRESSwasthenputforthbyBocquetetal.
andoftenincludeshepatitis,pericarditis,interstitialnephritis,orinterstitialpneumonitis[1,12].
IsolatedelevationoflivertransaminasesisthemostcommonlaboratorymanifestationofhepatitisinDRESSsyndrome.
Inseverecasesitcanprogresstofulminantliverfailure,occurringinasmanyas10%ofcasesandaccountingfortheprinciplecauseofmortalityinpatientsaffectedbyDRESSsyndrome[1].
AlthoughthepathophysiologyofDRESSsyndromeremainsunknown,eosinophilicinfiltrationisprobablythemechanismforinvolvementoforganssuchastheliverandkidneys[2].
Promptrecognitionandremovaloftheoffendingagentisthekeytolimitingfurtherhepaticdamage,althoughhepatitismaysignificantlyworsenevenafterdiscontinuationofthedrugandmaytakemonthstoresolvecompletely.
Althoughnorandomized-controlledtherapytrialshavebeendone,corticosteroidsareutilizedinmanyreportedcases[3-5,8].
Nospecifictherapeuticregimenordosinghasbeenshowntobemorebeneficialthananother,butitisimportantthattherapyiscontin-uedforlongenoughinordertopreventthepossibilityofrelapse.
Thefollowingcasereportdemonstratesthenecessityofpromptrecognitionandinitiationofappro-priatetherapyinpreventingthepotentialsequelaeofDRESSsyndrome.
CasepresentationAn18-year-oldAfrican-Americanmanpresentedwithafive-dayhistoryofpruritic,maculopapularrashwithassociatedperiorbitalswelling,fever,andtransaminitis.
Fivedayspriortopresentationhenotedpruritisandrashoverhisextremities,whichoverthenextseveraldaysprogressedtohischest,back,andface.
Hehadahistoryofseizuresthatbegan35dayspriortothisadmissiontreatedwithphenytoinextended-releaseER100mgdailyandlevetiracetam500mgtwiceaday.
Afterinvestigation,nospecificfocusoretiologyofhisseizureshadbeenidentified.
Hehashaddecreasedverbalandreadingskillssinceearlychildhood,butdetailsabouthisdeliveryandearlydevelopmentareunclearbecausehewasadopted.
Thepatienthadnoothersignificantpastmedicalhistory,drugallergies,oralcoholuse.
Reviewofsystemswaspositivefornon-productivecough,fever,andtea-coloredurine,andnegativeforchestpain,ab-dominalpain,shortnessofbreath,nausea,vomiting,weight-loss,chills,oranyrecentalteredmentalstatus.
Onexamination,thepatientwasfebrileto40.
2°C(104.
4°F)withaheartrateof88beats/minute,respira-toryrateof18,andbloodpressureof110/55mmHg.
Thepatientwaswellnourished,welldeveloped,alertandwelloriented,andappeareduncomfortablebutnotindistress.
Afineexanthematousrashwasnotedontheface,upper,andlowerextremitiesinsun-exposedareaswithoutinvolvementoftheoralmucosa,palms,orsoles.
Therewasprofoundperiorbitaledemathatpreventedeye-opening.
Hisabdomenwassoftandnon-distendedwithnotenderness,guarding,orhepatosplenomegaly.
Nofocaldeficitswereappreciatedonneurologicalexam-ination.
Atthispointthedifferentialdiagnosisincludeddrug-inducedhypersensitivity,erythemamultiforme,toxicepidermalnecrolysis,vasculitis,anexanthemduetoviralinfectionsuchasEpstein–Barrvirus(EBV),cyto-megalovirus(CMV),andhumanimmunodeficiencyvirus(HIV),andauto-immuneconditionssuchassystemiclupuserythematosus.
Laboratoryresultsrevealedawhitebloodcellcountof7.
9thousand/mm3(normalfrom4.
0to10.
0thousand/mm3),with60%neutrophils,8.
0%lymphocytes,and4.
0%eosinophils(absolute0.
32thousand/mm[3]).
Hisfreephenytoinlevelonadmissionwas0.
4mcg/mL(therapeuticfrom1.
0to2.
0mcg/mL).
Hisbasicmetabolicpanelwaswithinnormallimits.
Hepaticfunctionpanelrevealedanaspartateaminotransferaseof778U/L(normalfrom0to37),andalanineaminotransferase(ALT)of1274U/L(normalfrom0to41).
Acetaminophenandsalicylatelevelswerebelowdetectablelimits.
EvaluationforacuteandchronichepatitiswithserologieswasnegativeforhepatitisA,B,andC.
Anextensiveworkupwasperformedincludingelectrocardiogramandechocardiogramwhichwerenegativeforabnormalities.
EBV,CMV,andHIVTable1DruggroupscommonlyassociatedwithdrugreactionwitheosinophiliaandsystemicsymptomssyndromeDrugGroups:SpecificExamples:Anticonvulsantsphenytoin,carbamazepine,phenobarbital,lamotrigine,valproateAntidepressantsdespiramine,amitriptyline,fluoxetineSulfonamides/sulfonesdapsone,sulfasalazine,trimethoprim-sulfamethoxazoleAnti-inflammatoriespiroxicam,naproxen,diclofenac,sulindac,ibuprofenAnti-infectivesabacavir,nevirapine,linezolid,doxycycline,nitrofurantoinAngiotensin-convertingenzymeinhibitorscaptopril,enalaprilBeta-blockersatenolol,celiprololHallandFrommJournalofMedicalCaseReports2013,7:2Page2of5http://www.
jmedicalcasereports.
com/content/7/1/2testingwereallnegative,asweretheresultsoftestsforantinuclearantibodies(ANA).
Thepatientwasadmittedtoourhospitalwithapresumptivediagnosisofdrug-inducedhypersensitivity.
Allmedicationswerediscontin-uedandthepatientwasmonitoredforsignsofclinicalrecovery.
Onhospitalday1,thepatient'sconditionworsenedwithincreasedfacialswellingandrashextendingtohischestandabdomen.
Hebegantoshowsignsofliversyntheticdysfunctionwithanelevatedprothombintimeandinternationalnormalizedratioaswellasanin-creasingtransaminitis.
Arepeatcompletebloodcountshowedanatypicallymphocytosisandeosinophiliaat8.
0%.
Becauseofhisdeterioratingcondition,thepatientwasstartedondexamethasone4mgorallyfourtimesdaily.
Onhospitalday2,thepatientshowedamarkedclinicalrecovery.
Despiteimprovementinthepatient'srash,hislevelsoftransaminasescontinuedtoclimb,necessitatinghepatologyconsultationtoassistwithevaluationfortransplantation.
Onhospitalday3hislevelsoftransaminasesbegantoimprove,andbyday8histransaminitishadsubstantiallyresolved(Figure1)andhewasdischargedhomeonprednisone50mgtobetakenonceadayuntilfollow-upwithahepatologist.
Follow-upfivemonthsafterdischargerevealedthatthepatientwasdoingwellwithnorecurrenceofhisrashorothersymptoms,noseizures,andnormalizationofhisserumtransaminases.
Heexperiencednoflareaftercorticosteroidtaperingorwithdrawalandtodatehasnothadanyhepaticsequelae.
DiscussionDRESSsyndromeisanoftenunder-diagnosedandunder-recognizedseveretypeIV(delayedtype)hypersensitivityreactionthatcanoccurwithanymedicationbutmostcommonlyinresponsetoaromaticanticonvulsants[1,2,6,9,10,12,13].
Likemostsevereallergicreactions,DRESSsyndromeinvolvesrash,diffuseswelling,aswellaseosinophilia[1,2,11,14].
ThehallmarkofDRESSsyn-drome,however,isthepresenceofsystemicmanifesta-tionssuchasinflammationoftheliver,kidneys,heart,orotherorgans[1,12,13].
Althoughnoformaldiagnosticcriteriahavebeenwidelyaccepted,aJapaneseworkinggroupin2007establishedasetofdiagnosticguidelinesrequiringthefollowing:first,maculopapularrashdevelop-inggreaterthanthreeweeksafterstartingadrug;second,prolongedclinicalsymptomstwoweeksafterdiscontinu-ationofthecausativedrug;third,fevergreaterthan38°C;fourth,liverabnormalities(includingALTgreaterthan100U/L);fifth,leukocyteabnormalities(eitherleukocytosisgreaterthan11*109/L,anatypicallymphocytosis,oreosinophiliagreaterthan1.
5*109/L);sixth,lymphadenop-athy;andseventh,humanherpesvirus6(HHV-6)reactiva-tion[2].
ThepatientdescribedheremetallofthesedescribedcriteriaforadiagnosisofDRESS.
Althoughhehadnopalpablelymphadenopathy,anabdominalcom-putedtomographyscanconfirmedprofoundretrope-ritoneallymphnodeenlargement.
Finally,aqualitativedeoxyribonucleicacid(DNA)assayrevealedthepresenceofHHV-6typeBinthepatient'sblood,indicatingthereactivationofHHV-6associatedwiththepatient'sDRESSsyndrome[2,15,16].
Alternatively,Kardaunetal.
oftheSevereCutaneousAdverseReactions(RegiSCAR)studygrouppublishedascoringsystemin2007whichhasalsobeenwidelyusedtoevaluatepotentialcasesofDRESSsyndrome[14].
Thecriteriaforthissysteminclude:first,fevergreaterthan38.
5°C;second,enlargedlymphnodes;third,eosino-philia;fourth,atypicallymphocytosis;fifth,skininvolve-ment;sixth,organinvolvement;seventh,resolutiongreaterthan15days;andeighth,evaluationofothercauses(ANA,bloodcultures,serologyforhepatitisAvirus,hepatitisBvirus,hepatitisCvirus,andchlamydiaand/ormycoplasma).
Usingthisscoringsystem,afinalscoreoflessthantwoindicatesnocase,afinalscoreofbetweentwoandthreeindicatesapossiblecase,afinalscoreofbetweenfourandfiveindicatesaprobablecase,andafinalscoreofgreaterthanfiveindicatesadefinitecase.
Thepatientinthiscasereporthadascoreofsixpoints(oneeachforlymphadenopathy,eosinophilia,atypicallymphocytosis,skinrashsuggestiveofDRESS,liverinvolvement,andevaluationofotherpotentialcauses),indicatinga'definitecase'ofDRESSpertheRegiSCARscoringguidelines.
Animportantquestiontoconsideriswhichmedicationwasactuallythesourceofthepatient'sreaction,ashehadbeenstartedonphenytoinandlevetiracetamwithindaysofeachotherduetorecurringseizuresonphenytoinFigure1Serummeasurementsofalanineaminotransferase(ALT)andaspartateaminotransferase(AST)duringthepatient'sadmission.
Normalreferencerangesarefrom0to41U/LforALTandfrom0to37U/LforAST.
Day0(*)representsthedayofadmissionanddiscontinuationofphenytoin.
CorticosteroidtherapywasbegunonDay2(**).
HallandFrommJournalofMedicalCaseReports2013,7:2Page3of5http://www.
jmedicalcasereports.
com/content/7/1/2alone.
AlthoughDRESSwasoriginallydescribedinresponsetophenytoinandithasbeenoneofthemostcommoncausativemedications,Gómez-Zorrillaetal.
publishedacasereportearlierthisyear(2012)ofapatientpresentingwithDRESSsyndromewhotooknomedica-tionsotherthanlevetiracetam[6,7,11].
Ifthepatientweretoagainrequireanticonvulsanttherapy,itwouldbeprudenttoavoiduseofbothphenytoinandlevetiracetam,andtooptinsteadforanalternativenon-aromaticanticonvulsant.
PromptrecognitionoftheadversedrugreactionanddiscontinuationofoffendingmedicationareimperativestepsinlimitingtheprogressionofDRESSsyndrome.
PharmacologicaltreatmentofDRESSsyndromehastodatenotbeenstudiedwithrandomizedcontrolledtrialsandinsteadhasbeenestablishedonthebasisofcasereportsandretrospectiveanalysis.
Systemiccorticoste-roidshavebecomeamainstayoftherapyinseverecasesandoftenproducemarkedimprovementinclinicalsymptomsandlaboratorymeasuresinjustafewdaysaftertheinitiationoftreatment[3-5,8].
Ifsymptomscontinuetoprogressdespitetheuseofcorticosteroids,otheroptionsincludeintravenousimmunoglobulin(IVIG)and/orplasmapheresis[6].
TheFrenchSocietyofDermatologypublishedareportin2010outliningaconsensusontherapeuticmana-gementofDRESS[17].
Theyrecommendtheuseofsystemiccorticosteroidsatadoseequivalenttoonemg/kg/dayofprednisoneinpatientswithanysignofseverityincluding:transaminasesgreaterthanfivetimesnormal,renalinvolvement,pneumonia,hemophagocytosis,orcardiacinvolvement.
TheyfurtherrecommendtheuseofIVIGatadoseoftwog/kgoverfivedaysforapatientwithlife-threateningsignssuchasrenalfailureorres-piratoryfailure.
Inaddition,theyproposetheuseofsteroidsincombinationwithganciclovirinpatientswithsignsofseverityandconfirmationofamajorviralreacti-vationofHHV-6.
However,becauseanti-HHV-6im-munoglobulinGtitersarenotcurrentlywidelyavailableinallhospitalsandlaboratories,resultsoftentakeseve-raldaysorweekstoconfirmviralreactivation.
BecausetimeisanimportantfactorinthetreatmentofDRESS,itisnotrecommendedtodelaydefinitivetherapyinordertoconfirmamajorviralreactivation.
Furtherstudyandrandomizedcontrolledtrialsoftheseandotherpotentialpharmacologictherapieswillbeimpor-tantinestablishingastandardofcareandtoimproveunderstandingofhowbesttotreatpatientsaffectedbyDRESSsyndrome.
ConclusionGiventhesignificantmortalityattributedtoDRESSsyndrome,cliniciansshouldbeawareofthepotentialforthisseverehypersensitivityreactionparticularlyinstartinganynewanti-epilepticmedication.
Inpatientspresentingwithskinrashandsystemicabnormalitiesafterarecentchangeinmedications,physiciansshouldconsiderDRESSsyndromeasapossiblediagnosisandswitchtomoreaggressivetherapyifremovaloftheoffendingagentdoesnotresultinclinicalimprovement.
FurtherstudyofpotentialpharmacologicaltherapiesiswarrantedgiventhesignificantmorbidityassociatedwithDRESSsyndrome.
ConsentWritteninformedconsentwasobtainedfromthepatientandhislegalguardianforpublicationofthiscasereportandanyaccompanyingimages.
Acopyofthewrittencon-sentisavailableforreviewbytheEditor-in-Chiefofthisjournal.
CompetinginterestsTheauthorsdeclarethattheyhavenocompetinginterests.
Authors'contributionsDHanalyzedandinterpretedthedataregardingthepatient'sconditionandwrotethefirstdraftofthemanuscript.
JFexaminedandadministeredtreatmenttothepatientandwasamajorcontributorinwritingandeditingthemanuscript.
Bothauthorsreadandapprovedthefinalmanuscript.
Authordetails1CollegeofMedicine,UniversityofFloridaCollegeofMedicine,1600SWArcherRoad,POBox100277,Gainesville,FL32610-0277,USA.
2DepartmentofMedicine,UniversityofFloridaCollegeofMedicine,1600SWArcherRoad,POBox100277,Gainesville,FL32610-0277,USA.
Received:17August2012Accepted:22November2012Published:3January2013References1.
BocquetH,BagotM,RoujeauJC:Drug-inducedpseudolymphomaanddrughypersensitivitysyndrome(DrugRashwithEosinophiliaandSystemicSymptoms:DRESS).
SeminCutanMedSurg1996,15:250–257.
2.
ShioharaT,IijimaM,IkezawaZ,HashimotoK:ThediagnosisofDRESSsyndromehasbeensufficientlyestablishedonthebasisoftypicalclinicalfeaturesandviralreactivations.
ResponseBrJDermatol2007,156:1045–1092.
3.
VautheyL,UckayI,AbrassartS,BernardL,AssalM,FerryT,DjordjevicM,RoussosC,VaudauxP:Vancomycin-inducedDRESSsyndromeinafemalepatient.
Pharmacology2008,82:138–141.
4.
SavardS,DesmeulesS,RiopelJ,AgharaziiM:Linezolid-associatedacuteinterstitialnephritisanddrugrashwitheosinophiliaandsystemicsymptoms(DRESS)syndrome.
AmJKidneyDis2009,54:e17–e20.
5.
VelemaMS,VoermanHJ:DRESSsyndromecausedbynitrofurantoin.
NethJMed2009,67:147–149.
6.
CriadoPR,CriadoRF,JdeAvanciniM,SantiCG:DrugreactionwithEosinophiliaandSystemicSymptoms(DRESS)/Drug-inducedHypersensitivitySyndrome(DIHS):areviewofcurrentconcepts.
AnBrasDermatol2012,87(3):435–449.
7.
Gómez-ZorrillaS,FerrazAV,PedrósC,LemusM,PeaC:Levetiracetam-induceddrugreactionwitheosinophiliaandsystemicsymptomssyndrome.
AnnPharmacother2012,46(7–8):e20.
8.
TennisP,StemRS:Riskofseriouscutaneousdisordersafterinitiationofuseofphenytoin,carbamazepine,orsodiumvalproate:arecordlinkagestudy.
Neurology1997,49:542–546.
9.
CarrollMC,Yueng-YueKA,EsterlyNB,DroletBA:Drug-inducedhypersensitivitysyndromeinpediatricpatients.
Pediatrics2001,108(2):485–492.
10.
Benm'radM,Leclerc-MercierS,BlancheP,FranckN,RozenbergF,FullaY,GuesmiM,RollotF,DehouxM,GuillevinL,MoachonL:Drug-inducedHallandFrommJournalofMedicalCaseReports2013,7:2Page4of5http://www.
jmedicalcasereports.
com/content/7/1/2hypersensitivitysyndrome:clinicalandbiologicdiseasepatternsin24patients.
Medicine(Baltimore)2009,88:131–140.
11.
ChaikenBH,GoldbergBI,SegalJP:Dilantinsensitivity;reportofacaseofhepatitiswithjaundice,pyrexiaandexfoliativedermatitis.
NEnglJMed1950,242(23):897–898.
12.
CacoubP,MusetteP,DescampsV,MeyerO,SpeirsC,FinziL,RoujeauJC:TheDRESSsyndrome:aliteratureoverview.
AmJMed2011,124(7):588–597.
13.
FrielingG,JessupC,MihmM:Drugrashwitheosinophiliaandsystemicsymptoms.
InDiagnosticPathology:Non-neoplasticDermatopathology.
1stedition.
EditedbyHallBJ,HallJC,CockerellCJ.
SaltLakeCity,UT:AmirsysPublishing,Inc;2012:10–11.
14.
KardaunSH,SidoroffA,Valeyrie-AllanoreL,HalevyS,DavidoviciBB,MockenhauptM,RoujeauJC:Variabilityintheclinicalpatternofcutaneousside-effectsofdrugswithsystemicsymptoms:doesaDRESSsyndromereallyexistBrJDermatol2007,156(3):609–611.
15.
SuzukiY,InagiR,AonoT,YamanishiK,ShioharaT:Humanherpesvirus6infectionasariskfactorforthedevelopmentofseveredrug-inducedhypersensitivitysyndrome.
ArchDermatol1998,134:1108–1112.
16.
KanoY,InaokaM,ShioharaT:Associationbetweenanticonvulsanthypersensitivitysyndromeandhumanherpesvirus6reactivationandhypogammaglobulinemia.
ArchDermatol2004,140:183–188.
17.
DescampsV,Ben-SadB,SassolasB,TruchetetF,Avenel-AudranM,GirardinP,GuinnepainMT,Mathelier-FusadeP,AssierH,MilpiedB,ModianoP,Lebrun-VignesB,BarbaudA,groupeToxidermiesdelaSociétéfranaisededermatologie:Managementofdrugreactionwitheosinophiliaandsystemicsymptoms(DRESS).
AnnDermatolVenereol2010,137:703–708.
doi:10.
1186/1752-1947-7-2Citethisarticleas:HallandFromm:Drugreactionwitheosinophiliaandsystemicsymptomssyndromeinapatienttakingphenytoinandlevetiracetam:acasereport.
JournalofMedicalCaseReports20137:2.
SubmityournextmanuscripttoBioMedCentralandtakefulladvantageof:ConvenientonlinesubmissionThoroughpeerreviewNospaceconstraintsorcolorgurechargesImmediatepublicationonacceptanceInclusioninPubMed,CAS,ScopusandGoogleScholarResearchwhichisfreelyavailableforredistributionSubmityourmanuscriptatwww.
biomedcentral.
com/submitHallandFrommJournalofMedicalCaseReports2013,7:2Page5of5http://www.
jmedicalcasereports.
com/content/7/1/2
Thepresentcaseisanexampleofsevereandpotentiallylife-threateninghepatitisasamanifestationofdrugreactionwitheosinophiliaandsystemicsymptomssyndrome.
Casepresentation:Wereportacaseofanti-epileptic-induceddrugreactionwitheosinophiliaandsystemicsymptomssyndromeinan18-year-oldAfrican-Americanmanwhopresentedwithafive-dayhistoryofrash,periorbitalandupperextremityedema,hepatitisandfever.
Laboratoryfindingsrevealedanatypicallymphocytosis,eosinophilia,andelevatedserumtransaminases.
Nodrugallergieswerereportedatthetimeofpresentation,butphenytoinandlevetiracetamtherapyhadbeeninitiatedfiveweekspriortohospitaladmissionfornew-onsetseizures.
Bothmedicationswerediscontinuedonhospitaladmission,andafterthreedaysofhigh-dosecorticosteroidtherapythepatientexperiencedresolutionofbothhissymptomsandlaboratorymarkersofinflammation.
Conclusion:Giventhesignificantmortalityattributedtodrugreactionwitheosinophiliaandsystemicsymptomssyndrome,medicalpersonnelshouldbeawareofthepotentialforthisseverehypersensitivityreactionandshouldensureclosefollow-upandofferanticipatoryguidancewhenbeginninganynewmedication,particularlyanti-epileptictherapy.
Earlyrecognitionofdrugreactionwitheosinophiliaandsystemicsymptomssyndromeandinitiationofappropriatetherapyareimperativeinlimitingmorbidity.
Keywords:Allergy,Anti-epileptic,DRESSsyndrome,Hepatitis,Hypersensitivityreaction,LevetiracetamPhenytoin,RashIntroductionDrugreactionwitheosinophiliaandsystemicsymptoms(DRESS)syndrome,alsoknownasdrug-inducedhy-persensitivitysyndrome(DIHS),isanunder-recognizedandpotentiallylife-threateninghypersensitivityreactionassociatedwithavarietyofmedications,manybeinganti-epileptics.
PatientswithDRESSsyndrometypicallypresentwithrash,swelling,fever,andsystemicmanifes-tationssuchasaseveretransaminitis[1].
Inmostcases,apatient'sface,trunk,andupperextremitiesareaffectedbyarashwhichisatfirstmorbilliformthengraduallytransitionstomaculopapular,andfinallycanprogresstoedemaoftheface,particularlyintheperiorbitalregion.
Althoughrashandeosinophiliaarecommonlyseeninhypersensitivityreactions,thedefiningcharacteristicofDRESSsyndromeisorgandysfunction,mostcommonlyoftheliver,kidneys,heart,orlungs.
Thesepatientsaretypicallyfoundtohavestartedoneofafewselectmedi-cationsinthepasttwotoeightweeks(Table1)witharo-maticanti-epilepticsbeingthemostcommonlyimplicated[2-6].
Non-aromaticanti-epilepticmedica-tionssuchasatopiramate,ethosuximide,andlevetirace-tamweretraditionallythoughttobesafer;however,arecentcasereportdescribedDRESSsyndromeinapa-tienttakingonlylevetiracetam[7].
Althoughthetruein-cidenceisunknown,DRESSsyndromehasbeen*Correspondence:jason.
fromm@medicine.
ufl.
edu2DepartmentofMedicine,UniversityofFloridaCollegeofMedicine,1600SWArcherRoad,POBox100277,Gainesville,FL32610-0277,USAFulllistofauthorinformationisavailableattheendofthearticleJOURNALOFMEDICALCASEREPORTS2013HallandFromm;licenseeBioMedCentralLtd.
ThisisanOpenAccessarticledistributedunderthetermsoftheCreativeCommonsAttributionLicense(http://creativecommons.
org/licenses/by/2.
0),whichpermitsunrestricteduse,distribution,andreproductioninanymedium,providedtheoriginalworkisproperlycited.
HallandFrommJournalofMedicalCaseReports2013,7:2http://www.
jmedicalcasereports.
com/content/7/1/2estimatedtooccurinapproximatelyoneoutof1000to10,000newusersofanti-epilepticmedicationsandismorecommonlyreportedinAfrican-Americanmen[1,8,9].
VitaminDdeficiencyhasbeenimplicatedasapossiblecontributortothepathogenesisofDRESSduetoitsprotectiveeffectsagainstinflammatoryandauto-immuneconditions,andbecausevitaminDdeficiencyoccursmorefrequentlyinpeoplewithdarkerskinphenotypes[10].
DIHSwasoriginallydescribedin1950byChaikenetal.
asatriadoffever,rash,andmulti-organfailure[11].
TheacronymDRESSwasthenputforthbyBocquetetal.
andoftenincludeshepatitis,pericarditis,interstitialnephritis,orinterstitialpneumonitis[1,12].
IsolatedelevationoflivertransaminasesisthemostcommonlaboratorymanifestationofhepatitisinDRESSsyndrome.
Inseverecasesitcanprogresstofulminantliverfailure,occurringinasmanyas10%ofcasesandaccountingfortheprinciplecauseofmortalityinpatientsaffectedbyDRESSsyndrome[1].
AlthoughthepathophysiologyofDRESSsyndromeremainsunknown,eosinophilicinfiltrationisprobablythemechanismforinvolvementoforganssuchastheliverandkidneys[2].
Promptrecognitionandremovaloftheoffendingagentisthekeytolimitingfurtherhepaticdamage,althoughhepatitismaysignificantlyworsenevenafterdiscontinuationofthedrugandmaytakemonthstoresolvecompletely.
Althoughnorandomized-controlledtherapytrialshavebeendone,corticosteroidsareutilizedinmanyreportedcases[3-5,8].
Nospecifictherapeuticregimenordosinghasbeenshowntobemorebeneficialthananother,butitisimportantthattherapyiscontin-uedforlongenoughinordertopreventthepossibilityofrelapse.
Thefollowingcasereportdemonstratesthenecessityofpromptrecognitionandinitiationofappro-priatetherapyinpreventingthepotentialsequelaeofDRESSsyndrome.
CasepresentationAn18-year-oldAfrican-Americanmanpresentedwithafive-dayhistoryofpruritic,maculopapularrashwithassociatedperiorbitalswelling,fever,andtransaminitis.
Fivedayspriortopresentationhenotedpruritisandrashoverhisextremities,whichoverthenextseveraldaysprogressedtohischest,back,andface.
Hehadahistoryofseizuresthatbegan35dayspriortothisadmissiontreatedwithphenytoinextended-releaseER100mgdailyandlevetiracetam500mgtwiceaday.
Afterinvestigation,nospecificfocusoretiologyofhisseizureshadbeenidentified.
Hehashaddecreasedverbalandreadingskillssinceearlychildhood,butdetailsabouthisdeliveryandearlydevelopmentareunclearbecausehewasadopted.
Thepatienthadnoothersignificantpastmedicalhistory,drugallergies,oralcoholuse.
Reviewofsystemswaspositivefornon-productivecough,fever,andtea-coloredurine,andnegativeforchestpain,ab-dominalpain,shortnessofbreath,nausea,vomiting,weight-loss,chills,oranyrecentalteredmentalstatus.
Onexamination,thepatientwasfebrileto40.
2°C(104.
4°F)withaheartrateof88beats/minute,respira-toryrateof18,andbloodpressureof110/55mmHg.
Thepatientwaswellnourished,welldeveloped,alertandwelloriented,andappeareduncomfortablebutnotindistress.
Afineexanthematousrashwasnotedontheface,upper,andlowerextremitiesinsun-exposedareaswithoutinvolvementoftheoralmucosa,palms,orsoles.
Therewasprofoundperiorbitaledemathatpreventedeye-opening.
Hisabdomenwassoftandnon-distendedwithnotenderness,guarding,orhepatosplenomegaly.
Nofocaldeficitswereappreciatedonneurologicalexam-ination.
Atthispointthedifferentialdiagnosisincludeddrug-inducedhypersensitivity,erythemamultiforme,toxicepidermalnecrolysis,vasculitis,anexanthemduetoviralinfectionsuchasEpstein–Barrvirus(EBV),cyto-megalovirus(CMV),andhumanimmunodeficiencyvirus(HIV),andauto-immuneconditionssuchassystemiclupuserythematosus.
Laboratoryresultsrevealedawhitebloodcellcountof7.
9thousand/mm3(normalfrom4.
0to10.
0thousand/mm3),with60%neutrophils,8.
0%lymphocytes,and4.
0%eosinophils(absolute0.
32thousand/mm[3]).
Hisfreephenytoinlevelonadmissionwas0.
4mcg/mL(therapeuticfrom1.
0to2.
0mcg/mL).
Hisbasicmetabolicpanelwaswithinnormallimits.
Hepaticfunctionpanelrevealedanaspartateaminotransferaseof778U/L(normalfrom0to37),andalanineaminotransferase(ALT)of1274U/L(normalfrom0to41).
Acetaminophenandsalicylatelevelswerebelowdetectablelimits.
EvaluationforacuteandchronichepatitiswithserologieswasnegativeforhepatitisA,B,andC.
Anextensiveworkupwasperformedincludingelectrocardiogramandechocardiogramwhichwerenegativeforabnormalities.
EBV,CMV,andHIVTable1DruggroupscommonlyassociatedwithdrugreactionwitheosinophiliaandsystemicsymptomssyndromeDrugGroups:SpecificExamples:Anticonvulsantsphenytoin,carbamazepine,phenobarbital,lamotrigine,valproateAntidepressantsdespiramine,amitriptyline,fluoxetineSulfonamides/sulfonesdapsone,sulfasalazine,trimethoprim-sulfamethoxazoleAnti-inflammatoriespiroxicam,naproxen,diclofenac,sulindac,ibuprofenAnti-infectivesabacavir,nevirapine,linezolid,doxycycline,nitrofurantoinAngiotensin-convertingenzymeinhibitorscaptopril,enalaprilBeta-blockersatenolol,celiprololHallandFrommJournalofMedicalCaseReports2013,7:2Page2of5http://www.
jmedicalcasereports.
com/content/7/1/2testingwereallnegative,asweretheresultsoftestsforantinuclearantibodies(ANA).
Thepatientwasadmittedtoourhospitalwithapresumptivediagnosisofdrug-inducedhypersensitivity.
Allmedicationswerediscontin-uedandthepatientwasmonitoredforsignsofclinicalrecovery.
Onhospitalday1,thepatient'sconditionworsenedwithincreasedfacialswellingandrashextendingtohischestandabdomen.
Hebegantoshowsignsofliversyntheticdysfunctionwithanelevatedprothombintimeandinternationalnormalizedratioaswellasanin-creasingtransaminitis.
Arepeatcompletebloodcountshowedanatypicallymphocytosisandeosinophiliaat8.
0%.
Becauseofhisdeterioratingcondition,thepatientwasstartedondexamethasone4mgorallyfourtimesdaily.
Onhospitalday2,thepatientshowedamarkedclinicalrecovery.
Despiteimprovementinthepatient'srash,hislevelsoftransaminasescontinuedtoclimb,necessitatinghepatologyconsultationtoassistwithevaluationfortransplantation.
Onhospitalday3hislevelsoftransaminasesbegantoimprove,andbyday8histransaminitishadsubstantiallyresolved(Figure1)andhewasdischargedhomeonprednisone50mgtobetakenonceadayuntilfollow-upwithahepatologist.
Follow-upfivemonthsafterdischargerevealedthatthepatientwasdoingwellwithnorecurrenceofhisrashorothersymptoms,noseizures,andnormalizationofhisserumtransaminases.
Heexperiencednoflareaftercorticosteroidtaperingorwithdrawalandtodatehasnothadanyhepaticsequelae.
DiscussionDRESSsyndromeisanoftenunder-diagnosedandunder-recognizedseveretypeIV(delayedtype)hypersensitivityreactionthatcanoccurwithanymedicationbutmostcommonlyinresponsetoaromaticanticonvulsants[1,2,6,9,10,12,13].
Likemostsevereallergicreactions,DRESSsyndromeinvolvesrash,diffuseswelling,aswellaseosinophilia[1,2,11,14].
ThehallmarkofDRESSsyn-drome,however,isthepresenceofsystemicmanifesta-tionssuchasinflammationoftheliver,kidneys,heart,orotherorgans[1,12,13].
Althoughnoformaldiagnosticcriteriahavebeenwidelyaccepted,aJapaneseworkinggroupin2007establishedasetofdiagnosticguidelinesrequiringthefollowing:first,maculopapularrashdevelop-inggreaterthanthreeweeksafterstartingadrug;second,prolongedclinicalsymptomstwoweeksafterdiscontinu-ationofthecausativedrug;third,fevergreaterthan38°C;fourth,liverabnormalities(includingALTgreaterthan100U/L);fifth,leukocyteabnormalities(eitherleukocytosisgreaterthan11*109/L,anatypicallymphocytosis,oreosinophiliagreaterthan1.
5*109/L);sixth,lymphadenop-athy;andseventh,humanherpesvirus6(HHV-6)reactiva-tion[2].
ThepatientdescribedheremetallofthesedescribedcriteriaforadiagnosisofDRESS.
Althoughhehadnopalpablelymphadenopathy,anabdominalcom-putedtomographyscanconfirmedprofoundretrope-ritoneallymphnodeenlargement.
Finally,aqualitativedeoxyribonucleicacid(DNA)assayrevealedthepresenceofHHV-6typeBinthepatient'sblood,indicatingthereactivationofHHV-6associatedwiththepatient'sDRESSsyndrome[2,15,16].
Alternatively,Kardaunetal.
oftheSevereCutaneousAdverseReactions(RegiSCAR)studygrouppublishedascoringsystemin2007whichhasalsobeenwidelyusedtoevaluatepotentialcasesofDRESSsyndrome[14].
Thecriteriaforthissysteminclude:first,fevergreaterthan38.
5°C;second,enlargedlymphnodes;third,eosino-philia;fourth,atypicallymphocytosis;fifth,skininvolve-ment;sixth,organinvolvement;seventh,resolutiongreaterthan15days;andeighth,evaluationofothercauses(ANA,bloodcultures,serologyforhepatitisAvirus,hepatitisBvirus,hepatitisCvirus,andchlamydiaand/ormycoplasma).
Usingthisscoringsystem,afinalscoreoflessthantwoindicatesnocase,afinalscoreofbetweentwoandthreeindicatesapossiblecase,afinalscoreofbetweenfourandfiveindicatesaprobablecase,andafinalscoreofgreaterthanfiveindicatesadefinitecase.
Thepatientinthiscasereporthadascoreofsixpoints(oneeachforlymphadenopathy,eosinophilia,atypicallymphocytosis,skinrashsuggestiveofDRESS,liverinvolvement,andevaluationofotherpotentialcauses),indicatinga'definitecase'ofDRESSpertheRegiSCARscoringguidelines.
Animportantquestiontoconsideriswhichmedicationwasactuallythesourceofthepatient'sreaction,ashehadbeenstartedonphenytoinandlevetiracetamwithindaysofeachotherduetorecurringseizuresonphenytoinFigure1Serummeasurementsofalanineaminotransferase(ALT)andaspartateaminotransferase(AST)duringthepatient'sadmission.
Normalreferencerangesarefrom0to41U/LforALTandfrom0to37U/LforAST.
Day0(*)representsthedayofadmissionanddiscontinuationofphenytoin.
CorticosteroidtherapywasbegunonDay2(**).
HallandFrommJournalofMedicalCaseReports2013,7:2Page3of5http://www.
jmedicalcasereports.
com/content/7/1/2alone.
AlthoughDRESSwasoriginallydescribedinresponsetophenytoinandithasbeenoneofthemostcommoncausativemedications,Gómez-Zorrillaetal.
publishedacasereportearlierthisyear(2012)ofapatientpresentingwithDRESSsyndromewhotooknomedica-tionsotherthanlevetiracetam[6,7,11].
Ifthepatientweretoagainrequireanticonvulsanttherapy,itwouldbeprudenttoavoiduseofbothphenytoinandlevetiracetam,andtooptinsteadforanalternativenon-aromaticanticonvulsant.
PromptrecognitionoftheadversedrugreactionanddiscontinuationofoffendingmedicationareimperativestepsinlimitingtheprogressionofDRESSsyndrome.
PharmacologicaltreatmentofDRESSsyndromehastodatenotbeenstudiedwithrandomizedcontrolledtrialsandinsteadhasbeenestablishedonthebasisofcasereportsandretrospectiveanalysis.
Systemiccorticoste-roidshavebecomeamainstayoftherapyinseverecasesandoftenproducemarkedimprovementinclinicalsymptomsandlaboratorymeasuresinjustafewdaysaftertheinitiationoftreatment[3-5,8].
Ifsymptomscontinuetoprogressdespitetheuseofcorticosteroids,otheroptionsincludeintravenousimmunoglobulin(IVIG)and/orplasmapheresis[6].
TheFrenchSocietyofDermatologypublishedareportin2010outliningaconsensusontherapeuticmana-gementofDRESS[17].
Theyrecommendtheuseofsystemiccorticosteroidsatadoseequivalenttoonemg/kg/dayofprednisoneinpatientswithanysignofseverityincluding:transaminasesgreaterthanfivetimesnormal,renalinvolvement,pneumonia,hemophagocytosis,orcardiacinvolvement.
TheyfurtherrecommendtheuseofIVIGatadoseoftwog/kgoverfivedaysforapatientwithlife-threateningsignssuchasrenalfailureorres-piratoryfailure.
Inaddition,theyproposetheuseofsteroidsincombinationwithganciclovirinpatientswithsignsofseverityandconfirmationofamajorviralreacti-vationofHHV-6.
However,becauseanti-HHV-6im-munoglobulinGtitersarenotcurrentlywidelyavailableinallhospitalsandlaboratories,resultsoftentakeseve-raldaysorweekstoconfirmviralreactivation.
BecausetimeisanimportantfactorinthetreatmentofDRESS,itisnotrecommendedtodelaydefinitivetherapyinordertoconfirmamajorviralreactivation.
Furtherstudyandrandomizedcontrolledtrialsoftheseandotherpotentialpharmacologictherapieswillbeimpor-tantinestablishingastandardofcareandtoimproveunderstandingofhowbesttotreatpatientsaffectedbyDRESSsyndrome.
ConclusionGiventhesignificantmortalityattributedtoDRESSsyndrome,cliniciansshouldbeawareofthepotentialforthisseverehypersensitivityreactionparticularlyinstartinganynewanti-epilepticmedication.
Inpatientspresentingwithskinrashandsystemicabnormalitiesafterarecentchangeinmedications,physiciansshouldconsiderDRESSsyndromeasapossiblediagnosisandswitchtomoreaggressivetherapyifremovaloftheoffendingagentdoesnotresultinclinicalimprovement.
FurtherstudyofpotentialpharmacologicaltherapiesiswarrantedgiventhesignificantmorbidityassociatedwithDRESSsyndrome.
ConsentWritteninformedconsentwasobtainedfromthepatientandhislegalguardianforpublicationofthiscasereportandanyaccompanyingimages.
Acopyofthewrittencon-sentisavailableforreviewbytheEditor-in-Chiefofthisjournal.
CompetinginterestsTheauthorsdeclarethattheyhavenocompetinginterests.
Authors'contributionsDHanalyzedandinterpretedthedataregardingthepatient'sconditionandwrotethefirstdraftofthemanuscript.
JFexaminedandadministeredtreatmenttothepatientandwasamajorcontributorinwritingandeditingthemanuscript.
Bothauthorsreadandapprovedthefinalmanuscript.
Authordetails1CollegeofMedicine,UniversityofFloridaCollegeofMedicine,1600SWArcherRoad,POBox100277,Gainesville,FL32610-0277,USA.
2DepartmentofMedicine,UniversityofFloridaCollegeofMedicine,1600SWArcherRoad,POBox100277,Gainesville,FL32610-0277,USA.
Received:17August2012Accepted:22November2012Published:3January2013References1.
BocquetH,BagotM,RoujeauJC:Drug-inducedpseudolymphomaanddrughypersensitivitysyndrome(DrugRashwithEosinophiliaandSystemicSymptoms:DRESS).
SeminCutanMedSurg1996,15:250–257.
2.
ShioharaT,IijimaM,IkezawaZ,HashimotoK:ThediagnosisofDRESSsyndromehasbeensufficientlyestablishedonthebasisoftypicalclinicalfeaturesandviralreactivations.
ResponseBrJDermatol2007,156:1045–1092.
3.
VautheyL,UckayI,AbrassartS,BernardL,AssalM,FerryT,DjordjevicM,RoussosC,VaudauxP:Vancomycin-inducedDRESSsyndromeinafemalepatient.
Pharmacology2008,82:138–141.
4.
SavardS,DesmeulesS,RiopelJ,AgharaziiM:Linezolid-associatedacuteinterstitialnephritisanddrugrashwitheosinophiliaandsystemicsymptoms(DRESS)syndrome.
AmJKidneyDis2009,54:e17–e20.
5.
VelemaMS,VoermanHJ:DRESSsyndromecausedbynitrofurantoin.
NethJMed2009,67:147–149.
6.
CriadoPR,CriadoRF,JdeAvanciniM,SantiCG:DrugreactionwithEosinophiliaandSystemicSymptoms(DRESS)/Drug-inducedHypersensitivitySyndrome(DIHS):areviewofcurrentconcepts.
AnBrasDermatol2012,87(3):435–449.
7.
Gómez-ZorrillaS,FerrazAV,PedrósC,LemusM,PeaC:Levetiracetam-induceddrugreactionwitheosinophiliaandsystemicsymptomssyndrome.
AnnPharmacother2012,46(7–8):e20.
8.
TennisP,StemRS:Riskofseriouscutaneousdisordersafterinitiationofuseofphenytoin,carbamazepine,orsodiumvalproate:arecordlinkagestudy.
Neurology1997,49:542–546.
9.
CarrollMC,Yueng-YueKA,EsterlyNB,DroletBA:Drug-inducedhypersensitivitysyndromeinpediatricpatients.
Pediatrics2001,108(2):485–492.
10.
Benm'radM,Leclerc-MercierS,BlancheP,FranckN,RozenbergF,FullaY,GuesmiM,RollotF,DehouxM,GuillevinL,MoachonL:Drug-inducedHallandFrommJournalofMedicalCaseReports2013,7:2Page4of5http://www.
jmedicalcasereports.
com/content/7/1/2hypersensitivitysyndrome:clinicalandbiologicdiseasepatternsin24patients.
Medicine(Baltimore)2009,88:131–140.
11.
ChaikenBH,GoldbergBI,SegalJP:Dilantinsensitivity;reportofacaseofhepatitiswithjaundice,pyrexiaandexfoliativedermatitis.
NEnglJMed1950,242(23):897–898.
12.
CacoubP,MusetteP,DescampsV,MeyerO,SpeirsC,FinziL,RoujeauJC:TheDRESSsyndrome:aliteratureoverview.
AmJMed2011,124(7):588–597.
13.
FrielingG,JessupC,MihmM:Drugrashwitheosinophiliaandsystemicsymptoms.
InDiagnosticPathology:Non-neoplasticDermatopathology.
1stedition.
EditedbyHallBJ,HallJC,CockerellCJ.
SaltLakeCity,UT:AmirsysPublishing,Inc;2012:10–11.
14.
KardaunSH,SidoroffA,Valeyrie-AllanoreL,HalevyS,DavidoviciBB,MockenhauptM,RoujeauJC:Variabilityintheclinicalpatternofcutaneousside-effectsofdrugswithsystemicsymptoms:doesaDRESSsyndromereallyexistBrJDermatol2007,156(3):609–611.
15.
SuzukiY,InagiR,AonoT,YamanishiK,ShioharaT:Humanherpesvirus6infectionasariskfactorforthedevelopmentofseveredrug-inducedhypersensitivitysyndrome.
ArchDermatol1998,134:1108–1112.
16.
KanoY,InaokaM,ShioharaT:Associationbetweenanticonvulsanthypersensitivitysyndromeandhumanherpesvirus6reactivationandhypogammaglobulinemia.
ArchDermatol2004,140:183–188.
17.
DescampsV,Ben-SadB,SassolasB,TruchetetF,Avenel-AudranM,GirardinP,GuinnepainMT,Mathelier-FusadeP,AssierH,MilpiedB,ModianoP,Lebrun-VignesB,BarbaudA,groupeToxidermiesdelaSociétéfranaisededermatologie:Managementofdrugreactionwitheosinophiliaandsystemicsymptoms(DRESS).
AnnDermatolVenereol2010,137:703–708.
doi:10.
1186/1752-1947-7-2Citethisarticleas:HallandFromm:Drugreactionwitheosinophiliaandsystemicsymptomssyndromeinapatienttakingphenytoinandlevetiracetam:acasereport.
JournalofMedicalCaseReports20137:2.
SubmityournextmanuscripttoBioMedCentralandtakefulladvantageof:ConvenientonlinesubmissionThoroughpeerreviewNospaceconstraintsorcolorgurechargesImmediatepublicationonacceptanceInclusioninPubMed,CAS,ScopusandGoogleScholarResearchwhichisfreelyavailableforredistributionSubmityourmanuscriptatwww.
biomedcentral.
com/submitHallandFrommJournalofMedicalCaseReports2013,7:2Page5of5http://www.
jmedicalcasereports.
com/content/7/1/2
- nauseawww.aise.com相关文档
- chiffrewww.aise.com
- significancewww.aise.com
- Advanceswww.aise.com
- successwww
- www.aise.com怎么观看网页一些视频?
CUBECLOUD:香港服务器、洛杉矶服务器、全场88折,69元/月
CUBECLOUD(魔方云)成立于2016年,亚太互联网络信息中心(APNIC)会员,全线产品均为完全自营,专业数据灾备冗余,全部产品均为SSD阵列,精品网络CN2(GIA) CU(10099VIP)接入,与当今主流云计算解决方案保持同步,为企业以及开发者用户实现灵活弹性自动化的基础设施。【夏日特促】全场产品88折优惠码:Summer_2021时间:2021年8月1日 — 2021年8月8日香港C...
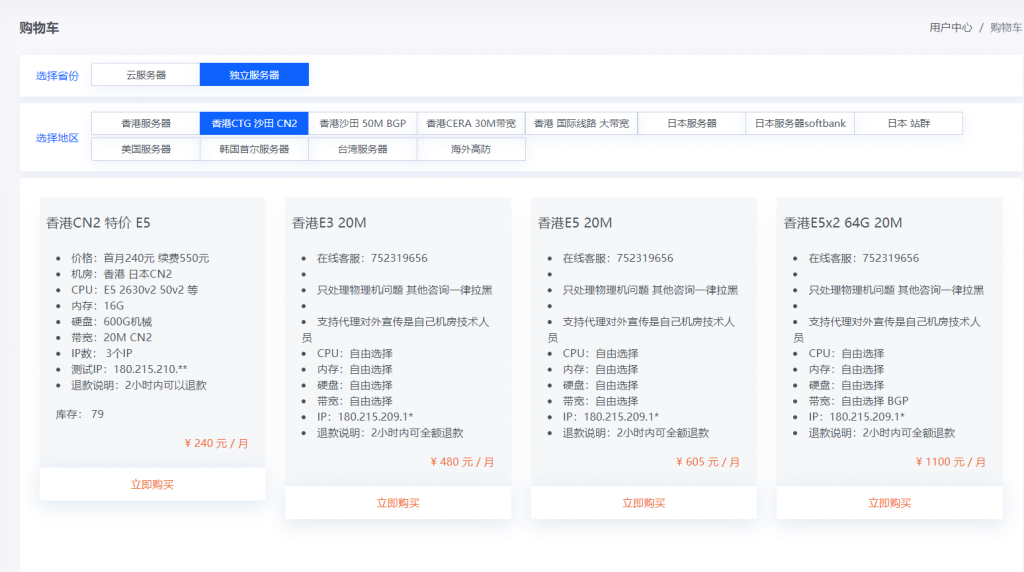
819云(240元)香港CN2 日本CN2 物理机 E5 16G 1T 20M 3IP
819云是我们的老熟人了,服务器一直都是稳定为主,老板人也很好,这次给大家带来了新活动,十分给力 香港CN2 日本CN2 物理机 E5 16G 1T 20M 3IP 240元0官方网站:https://www.819yun.com/ 特惠专员Q:442379204套餐介绍套餐CPU内存硬盘带宽IP价格香港CN2 (特价)E5 随机分配16G1T 机械20M3IP240元/月日本CN2 (...
pacificrack:VPS降价,SSD价格下降
之前几个月由于CHIA挖矿导致全球固态硬盘的价格疯涨,如今硬盘挖矿基本上已死,硬盘的价格基本上恢复到常规价位,所以,pacificrack决定对全系Cloud server进行价格调整,降幅较大,“如果您是老用户,请通过续费管理或升级套餐,获取同步到最新的定价”。官方网站:https://pacificrack.com支持PayPal、支付宝等方式付款VPS特征:基于KVM虚拟,纯SSD raid...
www.aise.com为你推荐
-
对对塔对对塔和魔方格那个是正宗的?rawtools闪迪32Gsd卡,无法格式化,显示只有30M,并且是raw格式。如何恢复?www.522av.com在白虎网站bhwz.com看电影要安装什么播放器?porndao单词prondao的汉语是什么www.765.com哪里有免费的电影网站www.5ff.comhttp://www.940777.com/网站,是不是真的网投六合www.123qqxx.com我的首页http://www.hao123.com被改成了http://www.669dh.cn/?yhcwww.mfav.org海关编码在线查询http://www.ccpit.org.c官人放题戴望舒的《狱中题壁》彪言彪语很多的话:( )言( )语 豪迈雄壮:( )言( )语 含有讽刺意味的风凉话:( )言( )语