lancewww.983mm.com
www.983mm.com 时间:2021-03-17 阅读:()
ORIGINALRESEARCHOpenAccessCombinedprevalenceofimpairedglucoselevelordiabetesanditscorrelatesinLusakaurbandistrict,Zambia:apopulationbasedsurveyMutaleNsakashalo-Senkwe1,SeterSiziya2*,FastoneMGoma3,PeterSongolo4,VictorMukonka1,OlusegunBabaniyi4AbstractBackground:Developingcountriesareundergoinganepidemiologicaltransition,fromCommunicableorInfectiousto'Non-Communicable'diseases(NCDs),suchthatcardiovasculardisease,chronicrespiratorydiseases,cancer,anddiabeteswereresponsiblefor60%ofalldeathsgloballyin2005,withmorethan75%ofthesedeathsoccurringindevelopingcountries.
Asurveywasconductedtodetermineamongotherobjectivestheprevalenceofdiabetesanditsassociationwithphysicalfitnessandbiologicalfactors.
Methods:AcrosssectionalstudyutilizingamodifiedWorldHealthOrganization'sSTEPwiseapproachtosurveillanceofNCDswasconductedinLusakadistrict,Zambia.
Amulti-stageclustersamplingtechniquewasusedtoselectstudyparticipantsofage25yearsorolder.
Alleligiblemembersofahouseholdthatwasselectedwereinvitedtoparticipateinthestudy.
Unadjustedoddsratios(OR),andadjustedoddsratios(AOR)togetherwiththeir95%ConfidenceIntervals(CI)wereobtainedusingComplexsampleslogisticregressionResults:Atotalof1928individualsparticipatedinthesurvey,ofwhich33.
0%weremales.
Abouthalfoftheparticipantswereofage25-34years(53.
2%),andaboutathirdoftherespondentshadattainedsecondarylevelofeducation(35.
8%).
Thecombinedprevalenceforimpairedglucoselevelordiabeteswas4.
0%.
Ageandmildhypertensionweresignificantlyassociatedwithimpairedlevelsofglucoseordiabetes.
Comparedtoparticipantsintheagegroup25-34years,olderparticipantsweremorelikelytohaveimpairedglucoselevelordiabetes(AOR=2.
49(95%CI[1.
35,2.
92])for35-44yearsagegroup,andAOR=3.
80(95%CI[2.
00,7.
23])for45+yearsagegroup).
Mildhypertensionwasassociatedwithimpairedglucoselevelordiabetes(AOR=2.
57)(95%CI[1.
44,4.
57])).
Conclusions:TheprevalenceofdiabetesinLusakadistricthasnotreachedanalarminglevelanditisnowthatinterventionstargetingtheyoungeragegroup25-34yearsshouldbeputinplacetocurtailthespreadofdiabetes.
BackgroundThemajorNon-CommunicableDiseases(NCDs)thatincludediabetescontributeimmenselytomortality[1].
AlltheNCDsareassociatedwithidentifiablebeha-viouralriskfactorsandbiologicalriskfactors.
Thesetwogroupsofriskfactorsarecloselylinked.
Themajorbehaviouralriskfactorsaretobaccouse,unhealthydietandphysicalinactivity[2].
Andthemajorbiologicalriskfactorsinclude;obesity,hypertension,diabetesanddyslipidemia[3];andgeneticpredispositionmainlyaccountingfortypeIdiabetes.
Mostofthesefactorsaremodifiablethroughlifestyleinterventions.
Workandlivingsituationshavebecomemoreseden-tarythusincreasingtheriskofNCDs[2].
Physicalinac-tivityincreasestheriskofmanychronicdiseases,suchastype2diabetes[4,5].
Metabolicsyndromewhichisagroupofdisordersthatincludeobesity,insulinresis-tance,glucoseintolerance,abnormallipidsandhyper-tensionhasbeenassociatedwithreducedphysicalactivities[6,7].
Lowphysicalactivitylikeprolongedtele-visionviewingmaycontributetometabolicsyndromethroughrelatedpooreatinghabits[4].
Severalstudies*Correspondence:ssiziya@yahoo.
com2DepartmentofCommunityMedicine,SchoolofMedicine,UniversityofZambia,Lusaka,ZambiaFulllistofauthorinformationisavailableattheendofthearticleNsakashalo-Senkweetal.
InternationalArchivesofMedicine2011,4:2http://www.
intarchmed.
com/content/4/1/22011Nsakashalo-Senkweetal;licenseeBioMedCentralLtd.
ThisisanOpenAccessarticledistributedunderthetermsoftheCreativeCommonsAttributionLicense(http://creativecommons.
org/licenses/by/2.
0),whichpermitsunrestricteduse,distribution,andreproductioninanymedium,providedtheoriginalworkisproperlycited.
haveshowedanassociationbetweenprolongedtelevi-sionviewingandmetabolicsyndrome[4,6].
Metabolicsyndromehasbeenlinkedtotype2Diabetesmellitus,cardiovasculardiseasesandmortalityandthereforereducingsedentarybehaviourhasaroleinthepreven-tionofthesechronicdiseases[4].
NelsonandGordon-Larsen[7]observedthatenhancingopportunitiesforincreasedexercisesandsportmayhaveabeneficialeffectinmodulatingriskbehavioursintheadolescentpopulation.
ThecontrolofNCDsincludingdiabeteshasreceivedlittleattention.
Forinstance,thereductionofNonCom-municablediseasesisnotaMillenniumDevelopmentGoal.
ManygovernmentsandorganisationshavefocussedoncontrollingdiseaseslikeHIV/AIDS,malariaandTuberculosis,andneglectingNCDs[8].
In2004,33.
1%ofmaleand32.
7%offemaleschoolgoingadolescentsofage13-15yearsinZambiareportedspendingthreeormorehoursduringatypicaldaysit-tingandwatchingtelevision,playingcomputergames,talkingwithfriends,ordoingothersittingactivities[9].
Nosimilarstudieshavebeenconductedamongnon-schoolgoingadolescentsoramongolderagegroups.
Asurveywasconductedtodetermineamongotherobjectivesthecombinedprevalenceofimpairedglucoselevelordiabetesanditsassociationwithphysicalfitnessandbiologicalfactors.
MethodsThestudywasconductedinLusakadistrictinlow,mediumandhighdensityresidentialareas.
Acrosssec-tionalstudyutilisingamodifiedWHOglobalsurveil-lanceinitiativeNCD-STEP3[10]wasusedinthecurrentstudy.
SamplesizeInastudywhoseresultsweredesignedtoreflectnationalestimates,atotalsamplesizeof6128respon-dentswascalculatedfortheentirecountry.
Thesamplesizewaspoweredenoughtoproduceestimatesforrural/urbancomparisons,andforbetweengenderanddistricts.
Lusakadistrictsamplesizewas1915participants.
SamplingAmulti-stageclustersamplingtechniquewasusedtoselectstudyparticipants.
LusakaprovincebeingthemosturbanisedprovinceinZambiawasconvenientlysampled.
Inthesecondstageofsampling,onlyLusakaurbandistrictwasconvenientlyselectedfromthethreedistrictsinLusaka(theothertwobeingKafuethatisaperi-urbandistrict;andChongwethatisaruraldistrict).
Lusakadistricthad7constituenciesoutofwhich5wererandomlyselected.
Fromeachselectedconstituency,onewardwasselected.
ThenumberofStandardEnumera-tionAreas(SEAs)selectedineachwardwaspropor-tionaltoitspopulationsize.
SEAswereselectedusingasystematicrandomsamplingmethod.
HouseholdswerethensystematicallysampledinordertowidelycovertheselectedSEAs.
Allpersonsofages25ormoreyearswereinvitedtoparticipateinthesurvey.
EthicalconsiderationsThestudyprotocolwasreviewedbytheUniversityofZambia(UNZA)ResearchEthicsCommittee(REC),andthestudyonlycommencedwhenapprovalfromtheUNZARECwasgranted.
AllentryformswerekeptintheofficeofthePrincipalInvestigator.
Entryformswereonlyviewedbyapprovedstudypersonnel.
DatacollectionTheWHOglobalsurveillanceinitiativeforNCD(WorldHealthOrganization,2005b)hasthreesteps:Step1isthequestionnaire,Step2isphysicalexaminations,andStep3isbiochemicalexaminations.
Allthesestepswereconductedwithintheparticipants'houses.
InterviewsAninterviewschedulewasusedtoelicitresponsesfromtheinterviewees.
Thequestionnairewasdividedintothefollowingsectionsamongothers:Demographicinforma-tion,Alcoholconsumption,Sedentarybehaviour(timeusuallyspentsittingorrecliningonatypicalday),Physi-calmeasurements(HeightandWeight,Waist,Bloodpressure,andHipcircumference)andBiochemicalmea-surements(Bloodglucose,andHDLcholesterol).
Inter-viewswereconductedinthehomesoftheparticipants.
MeasurementsTheWHOSTEPssurveillancetrainingandpracticalguiderecommendsthatphysicalmeasurementsbetakeninthefollowingorder:height,weight,waistcircumfer-ence,andbloodpressure.
Wechosetotakebloodpressurereadingsfirst,afterhavingadministeredthequestionnaire.
Thisgavetheparticipantenoughtimetohavesettleddown.
BloodpressureTheOmronDigitalAutomaticBPMonitorM4-1wasusedtomeasurethebloodpressureoftheparticipants.
Threeminutesofrestwasgiventotheparticipantinbetweenthreesuccessivereadingsofbloodpressure.
Althoughthethreereadingsweredifferentwiththelar-gestvaluebeingthefirstreadingandthesmallestbeingthethirdreadingonaverage,thesedifferedbynomorethan2mm/Hgofsystolicbloodpressure,andnomorethan4.
5mm/Hgofdiastolicbloodpressure.
Wechosetotakeanaverageofthethreereading,andnottheaverageofthesecondandthirdreadingsasrecom-mendedbyWorldHealthOrganisationinordertoincreasethedegreesoffreedomforthemean.
Nsakashalo-Senkweetal.
InternationalArchivesofMedicine2011,4:2http://www.
intarchmed.
com/content/4/1/2Page2of6Systolicbloodpressure(SBP)wasgroupedintofourlevels:1(raised).
Theana-lysisincludedrunningfrequencies,cross-tabulations,bivariate,andmultivariateComplexsampleslogisticregression.
Unadjustedoddsratios(OR),andadjustedoddsratios(AOR)togetherwiththeir95%CIwerecomputed.
ResultsAtotalof1928individualsparticipatedinthesurvey,ofwhich33.
0%weremales.
Abouthalfoftheparticipantswereofage25-34years(53.
2%),andathirdoftherespondentshadattainedsecondarylevelofeducation(35.
8%).
About1in5oftherespondentswereeitherselfemployed(22.
5%)orhousewives(20.
0%).
FurtherdescriptionofthesampleispresentedinTable1.
ImpairedglucoselevelordiabetesOfthetotalof1880subjectswhohadfastingbloodsugarmeasurementsdone,24(1.
3%)hadimpairedglu-coselevel(8males(33.
3%)and16females(66.
7%)while51(2.
7%)haddiabetes(13(25.
5%)malesand38(74.
5%)females).
Theagebysexstandardisedratesforcom-binedimpairedglucoselevelordiabetesformalesandfemalesconsideringLusaka'sagebysexpopulationwere4.
9%formalesand5.
6%forfemales.
Table2showsthedistributionofthecombinedpreva-lenceofimpairedglucoseordiabetesbyriskfactorsconsideredinthecurrentstudy.
Theprevalencevariedwithagewiththehighestprevalencebeingintheagegroup45+years.
Thehighestprevalencewasreportedamongparticipantswhowereobese.
ParticipantswithraisedcholesterolhadahigherprevalencethanNsakashalo-Senkweetal.
InternationalArchivesofMedicine2011,4:2http://www.
intarchmed.
com/content/4/1/2Page3of6thosewithnormallevelsofcholesterol.
Noclearpatternemergedfortheprevalenceamonglevelsofhypertension.
FactorsassociatedwithcombinedimpairedlevelsofglucoseordiabetesarepresentedinTable3.
Age,bodymassindex,waist-hipratio,hypertension,andcholes-terolweresignificantlyassociatedwithcombinedimpairedglucoselevelordiabetesinbivariateanalyses.
Inmultivariateanalysis,comparedtoparticipantsintheagegroup25-34years,olderparticipantsweremorelikelytohavecombinedimpairedglucoselevelordia-betes(AOR=2.
49(95%CI[1.
35,2.
92])for35-44yearsagegroup,andAOR=3.
80(95%CI[2.
00,7.
23])for45+yearsagegroup).
Onlymildhypertensionwasassociatedwithcombinedimpairedglucoselevelordiabetes(AOR=2.
57(95%CI[1.
44,4.
57])).
Nosignificantassociationswereobservedbetweenmoderateorseverehypertensionandcombinedimpairedglucoselevelordiabetes.
DiscussionThisisthefirststudytoreportresultsfromacompre-hensivegeneralpopulation-basedsurveyonthepreva-lencerateofimpairedglucoselevelordiabetesanditscorrelatesamongpersonsofage25yearsormoreinLusakaurbandistrict.
ThefindingsinthecurrentstudyformbaselineinformationtowhichinterventionstocontroldiabetesinLusakaurbandistrictcouldbemea-suredagainst.
Wefoundthattheprevalenceofdiabeteswas2.
1%amongmalesand3.
0%amongfemalesinthepresentstudy,andthatofimpairedglucoselevelwas1.
3%andTable1DemographiccharacteristicsforthesampledpopulationTotalMaleFemaleVariablen(%)n(%)n(%)Agegroup(years)25-341015(53.
2)337(53.
7)675(52.
9)35-44413(21.
6)135(21.
5)277(21.
7)45+481(25.
2)156(24.
8)323(25.
3)SexMale634(33.
0)--Female1288(67.
0)--EducationNone408(21.
5)76(12.
2)330(26.
0)Primary276(14.
5)61(9.
8)214(16.
9)Secondary679(35.
8)242(38.
8)435(34.
3)College/university534(28.
1)244(39.
2)290(22.
9)NB:numbersdonotaddupduetomissinginformation.
Table2DistributionofcombinedprevalenceofimpairedglucoselevelordiabetesbyriskfactorsconsideredinthecurrentstudyVariableTotaln(%)pvalueAgegroup(years)11510(*)Hypertension19.
57(3.
18,28.
83)HypertensionNormal11Mild4.
86(2.
76,8.
54)2.
57(1.
44,4.
57)Moderate2.
60(0.
96,7.
09)0.
98(0.
34,2.
83)Severe6.
77(3.
26,14.
02)1.
84(0.
75,4.
49)CholesterolNormal11Raised1.
85(1.
08,3.
19)1.
23(0.
67,2.
26)*notenoughdatainonecelltocomputetheestimateanditsconfidenceinterval.
Nsakashalo-Senkweetal.
InternationalArchivesofMedicine2011,4:2http://www.
intarchmed.
com/content/4/1/2Page5of6PossiblelimitationsThoughthestudydesignprovidesreliableandvalidinformation,thestudymayhavesomelimitations.
ThesurveywasdoneinLusakaurbandistrict,andhencetheresultscanonlybegeneralizedtothesampledpopula-tion.
Wedidnothavereliableinformationonthenum-berofhouseholdmembersofage25yearsorolderinordertoenableustocomputeresponserates.
Therefore,wecouldnotcomputeweightsthatcouldhavebeenusedintheanalysis.
Ourfindingsmaybebiasedtotheextentthatnon-respondentsdifferedfromthosethatpartici-patedinthesurvey.
However,weareunabletosuggestthedirectionofbias.
Someinformationontheimportantriskfactorsfordiabeteswaseithernotcollectedorinade-quatelycollected(suchasfamilyhistoryofdiabetesanddiet).
Weacknowledgelackofthisinformationasalim-itationtothestudythatmayhaveconfoundedourfind-ings.
Somestudyfactorsinoursurveywereobtainedthroughself-reports,andasinallsuchstudies,bothinad-vertentanddeliberatereportingisaconcern,moresothatweobtainedpersonalidentifiers.
Inspiteoftheabovelimitations,webelievethatourfindingsarecred-ibleastheycomparefavourablywiththoseobtainedintheZambiaDemographicandHealthSurvey.
ConclusionsTheprevalenceofdiabetesinLusakadistricthasnotreachedanalarminglevelanditisnowthatinterven-tionstargetingtheagegroups25-34yearsshouldbeputinplacetocurtailthespreadofdiabetes.
AcknowledgementsWegratefullythanktheNon-communicablediseases'steeringcommitteefordirectingtheentireresearchprocess;andtotheResearchassistantsfortheirtirelesseffortstosuccessfullycompletethesurvey.
WethankDrAggreyMweembaandDrGodfreyBiembafortheirinputintotheproposalwritingandpreparatoryworkofthestudy,respectively.
ThesurveywasfundedbytheMinistryofHealth,andtheWorldHealthOrganization.
Authordetails1DirectorateofPublicHealthandResearch,MinistryofHealth,Lusaka,Zambia.
2DepartmentofCommunityMedicine,SchoolofMedicine,UniversityofZambia,Lusaka,Zambia.
3DepartmentofPhysiology,SchoolofMedicine,UniversityofZambia,Lusaka,Zambia.
4WorldHealthOrganization,CountryOffice,Lusaka,Zambia.
Authors'contributionsMN-Scontributedtotheinterpretationofthefindings;SScontributedtothedesignofthestudy,trainingofresearchassistants,dataacquisition,dataanalysisandinterpretationofthefindings,andledthedraftingofthemanuscript;FMGcontributedtotrainingofinterviewers,dataacquisition,andinterpretationofthefindings;PScontributedtothedesignofthestudyandinterpretationofthefindings;VMcontributedtothedesignofthestudyandinterpretationofthefindings;OBcontributedtotheinterpretationofthefindings;Allauthorsreadandapprovedthefinalversionofthedocument.
CompetinginterestsTheauthorsdeclarethattheyhavenocompetinginterests.
Received:26August2010Accepted:12January2011Published:12January2011References1.
WorldHealthOrganization:Preventingchronicdisease:Avitalinvestment.
Geneva:WorldHealthOrganization;2005.
2.
WorleyH:Chronicdiseasesbeleaguerdevelopingcountries.
[http://www.
prb.
org/Articles/2006/ChronicDiseasesBeleaguerDevelopingCountries.
aspx].
3.
YusufS,ReddyS,OunpuuS,AnandS:GlobalburdenofcardiovasculardiseasesPartI:Generalconsideration,theepidemiologictransition,riskfactors,andimpactofurbanization.
Circulation2001,104:2746-2753.
4.
DunstanDW,SalmonJ,HealyGN,ShawJE,JolleyD,ZimmetPZ,OwenN,onbehalfoftheAusDiabSteeringCommittee:Associationoftelevisionviewingwithfastingand2-hourpostchallengeplasmaglucoselevelsinadultswithoutdiagnoseddiabetes.
DiabetesCare2007,30:516-522.
5.
BoothFW,ChakravarthyMV,GordonSE,SpangenburgEE:Wagingwaronphysicalinactivity:usingmodernmolecularammunitionagainstanancientenemy.
JApplPhysiol2002,93:3-30.
6.
GaoX,NelsonME,TuckerKL:TelevisionviewingisassociatedwithprevalenceofmetabolicsyndromeinHipanicelders.
DiabetesCare2007,30:694-700.
7.
NelsonMC,Gordon-LarsenP:Physicalactivityandsedentarybehaviorpatternsareassociatedwithselectedadolescenthealthriskbehaviors.
Pediatrics2006,117:1281-1290.
8.
HortonR:Theneglectedepidemicofchronicdisease.
Lancet2005,366(9496):1514.
9.
GlobalSchool-basedStudentHealthSurvey:Zambia2004factsheet.
[http://www.
who.
int/chp/gshs/Zambia%20fs%202004.
pdf].
10.
WorldHealthOrganization:WHOSTEPSSurveillanceManual:TheWHOSTEPwiseapproachtochronicdiseaseriskfactorsurveillance.
Geneva:WorldHealthOrganization;2005.
11.
MinistryofHealth[Nauru]:WorldHealthOrganization,CentreforPhysicalActivityandHealth[UniversityofSydney]:NauruNCDriskfactorsSTEPSreport2005.
Nauru:MinistryofHealth;2005.
12.
ElbagirMN,EltomMA,ElmahadiEM,KadamIM,BerneC:AhighprevalenceofdiabetesmellitusandimpairedglucoseintheDanaglacommunityinnorthernSudan.
DiabetMed1998,15:164-169.
13.
CharltonKE,LevittNS,LombardCJ:TheprevalenceofdiabetesmellitusandassociatedriskfactorsinelderlycolouredSouthAfrican.
SAfrMedJ1997,87:364-367.
14.
CuongT,DibleyM,BoweS,HanhT,LoanT:Obesityinadults:anemergingprobleminurbanareasofHoChiMinhCity,Vietnam.
EurJClinNutr2007,61:673-681.
15.
MinistryofHealth&ChildWelfare,UniversityofZimbabwe,WorldHealthOrganization,UnitedNationsChildren'sFund:NationalsurveyZimbabwenon-communicablediseaseriskfactors(ZiNCoDs)preliminaryreport2005:usingtheWHOSTEPwiseapproachtosurveillanceofnon-communicablediseases(STEPS).
[http://www.
who.
int/chp/steps/STEPS_Zimbabwe_Data.
pdf].
16.
MbanyaJC,KengneAP,AssahF:DiabetescareinAfrica.
Lancet2006,368(9548):1628-1629.
17.
ElbagirMN,EltomMA,ElmahadiEM,KadamIM,BerneC:Apopulation-basedstudyoftheprevalenceofdiabetesandimpairedglucosetoleranceinadultsinnorthernSudan.
DiabetesCare1996,19:1126-1128.
18.
RamaiyaKL,SwaiAB,McLartyDG,AlbertiKG:ImpairedglucosetoleranceanddiabetesmellitusinHinduIndianimmigrantsinDaresSalaam.
DiabetMed1991,8:738-744.
19.
PhamLH,AuTB,BlizzardL,TruongNB,SchmidtMD,GrangerRH,DwyerT:Prevalenceofriskfactorsfornon-communicablediseasesintheMekongDelta,Vietnam:resultsfromaSTEPSsurvey.
BMCPublicHealth2009,9:291.
doi:10.
1186/1755-7682-4-2Citethisarticleas:Nsakashalo-Senkweetal.
:CombinedprevalenceofimpairedglucoselevelordiabetesanditscorrelatesinLusakaurbandistrict,Zambia:apopulationbasedsurvey.
InternationalArchivesofMedicine20114:2.
Nsakashalo-Senkweetal.
InternationalArchivesofMedicine2011,4:2http://www.
intarchmed.
com/content/4/1/2Page6of6
- lancewww.983mm.com相关文档
- Waveformwww.983mm.com
- trademarkswww.983mm.com
- VOUTwww.983mm.com
- 点击www.983mm.com
- 1.238www.983mm.com
- peculiaritywww.983mm.com
RackNerd($199/月),5IP,1x256G SSD+2x3THDD
我们先普及一下常识吧,每年9月的第一个星期一是美国劳工节。于是,有一些服务商会基于这些节日推出吸引用户的促销活动,比如RackNerd有推出四款洛杉矶和犹他州独立服务器,1G带宽、5个独立IP地址,可以配置Windows和Linux系统,如果有需要独立服务器的可以看看。第一、劳工节促销套餐这里有提供2个套餐。两个方案是选择犹他州的,有2个方案是可以选择洛杉矶机房的。CPU内存SSD硬盘配置流量价格...
妮妮云(30元),美国300G防御 2核4G 107.6元,美国高速建站 2核2G
妮妮云的来历妮妮云是 789 陈总 张总 三方共同投资建立的网站 本着“良心 便宜 稳定”的初衷 为小白用户避免被坑妮妮云的市场定位妮妮云主要代理市场稳定速度的云服务器产品,避免新手购买云服务器的时候众多商家不知道如何选择,妮妮云就帮你选择好了产品,无需承担购买风险,不用担心出现被跑路 被诈骗的情况。妮妮云的售后保证妮妮云退款 通过于合作商的友好协商,云服务器提供2天内全额退款,超过2天不退款 物...
宝塔面板批量设置站点404页面
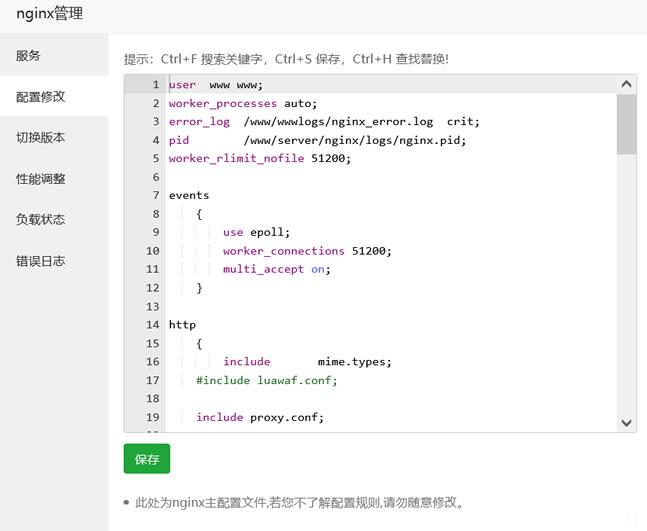
今天遇到一个网友,他在一个服务器中搭建有十几个网站,但是他之前都是采集站点数据很大,但是现在他删除数据之后希望设置可能有索引的文章给予404跳转页面。虽然他程序有默认的404页面,但是达不到他引流的目的,他希望设置统一的404页面。实际上设置还是很简单的,我们找到他是Nginx还是Apache,直接在引擎配置文件中设置即可。这里有看到他采用的是宝塔面板,直接在他的Nginx中设置。这里我们找到当前...
www.983mm.com为你推荐
-
杨紫别祝我生日快乐祝自己生日快乐内涵丰富的话咏春大师被ko咏春高手散打冠军林文学近况同ip网站查询同ip地址站点查询 我本地怎么查询不了haole10.com空人电影网改网址了?www.10yyy.cn是空人电影网么www.vtigu.com初三了,为什么考试的数学题都那么难,我最多也就135,最后一道选择,填空啊根本没法做,最后几道大题倒www.5any.com重庆哪里有不是全日制的大学?杨丽晓博客杨丽晓今年高考了吗?99nets.com制作网络虚拟证件的网站 那里有呀?kb123.net股市里的STAQ、NET市场是什么?本冈一郎本冈一郎有副作用吗?主要有什么呢?